
Category: Point of Care Ultrasound

  • Point-of-Care Ultrasound (POCUS) in Vascular Medicine & Vascular Surgery

    Point-of-Care Ultrasound (POCUS) in Vascular Medicine & Vascular Surgery

    Point-of-Care Ultrasound (POCUS) in Vascular Medicine and Vascular Surgery: See the Vessel, Understand the Flow, Guide the Procedure

    Bringing Vascular Ultrasound Directly to the Point of Care

    Vascular medicine is a specialty built around anatomy, circulation and blood flow.

    A patient may present with:

    Leg swelling.Point-of-Care Ultrasound (POCUS) in Vascular Medicine & Vascular Surgery
    Sudden limb pain.

    Varicose veins.

    Suspected Deep Vein Thrombosis (DVT).

    Poor peripheral circulation.

    A difficult vascular access.

    An arteriovenous fistula problem.

    Or a vascular surgeon may need to perform an ultrasound-guided endovenous intervention.

    In all of these situations, seeing the vessel can provide valuable information that physical examination alone cannot provide.

    This is where Point-of-Care Ultrasound (POCUS) is becoming increasingly relevant.

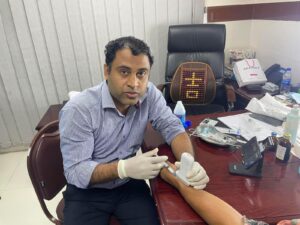
    POCUS allows an appropriately trained physician to perform a focused ultrasound examination at the bedside, outpatient chamber, procedure room or operating environment and immediately integrate the findings into clinical decision-making.

    A recent review of vascular POCUS describes its expanding use beyond procedural guidance, particularly for evaluation of lower-extremity deep venous thrombosis and the abdominal aorta.

    For vascular specialists, however, its potential goes even further.

    Vein. Artery. Flow. Needle. Catheter.

    POCUS puts vascular anatomy directly into the physician’s hands.


    What Is Vascular POCUS?

    Point-of-Care Ultrasound is generally a focused examination performed and interpreted by the treating clinician to answer a specific clinical question.

    For a vascular specialist, those questions may include:

    • Is this vein compressible? Point-of-Care Ultrasound (POCUS) in Internal Medicine
    • Is proximal DVT suspected?
    • Where is the target vein?
    • Where is the artery?
    • What is the diameter and depth of the vessel?
    • Which vessel is most appropriate for access?
    • Is blood flow visible with Color Doppler?
    • Is there a superficial venous abnormality?
    • Is the abdominal aorta enlarged?
    • Is an AV fistula accessible for cannulation?
    • Is there a collection, hematoma or suspected pseudoaneurysm?
    • Where should an endovenous catheter or needle be positioned?
    • What structures should be avoided during an intervention?

    This question-focused approach is different from a complete vascular laboratory duplex examination.

    POCUS is designed primarily to provide immediate, targeted information.


    Why POCUS Is Particularly Relevant to Vascular Specialists

    The vascular specialist works with structures that are highly suitable for ultrasound.

    Many important vessels are relatively superficial and can be clearly differentiated using B-mode and Doppler imaging.

    With ultrasound, the physician can potentially evaluate: 

    Vessel Anatomy

    Location, depth, diameter and relationship with surrounding structures.

    Compressibility

    Particularly relevant in venous thrombosis assessment.

    Blood Flow

    Using Color and spectral Doppler when appropriate.

    Needle Position

    During vascular access and other interventions.

    Surrounding Anatomy

    Including nerves, muscles, soft tissue and adjacent arteries or veins.

    This creates an important transition in vascular practice:

    From feeling the pulse to seeing the artery.

    From locating the vein by landmarks to visualizing it.

    From estimating needle position to guiding it in real time.


    1. Point-of-Care Ultrasound for Deep Vein Thrombosis

    Deep Vein Thrombosis is one of the most established diagnostic applications of vascular POCUS.

    Patients may present with:

    • Unilateral leg swelling Point-of-Care Ultrasound (POCUS) in Vascular Medicine & Vascular Surgery
    • Leg pain
    • Tenderness
    • Increased limb circumference
    • Risk factors for venous thromboembolism

    Clinical examination alone cannot reliably confirm or exclude DVT.

    Focused compression ultrasound can allow a trained physician to assess whether key proximal veins compress normally.

    The fundamental concept is simple:

    Normal vein → Usually compresses under appropriate probe pressure.

    Thrombosed vein → May fail to compress normally.

    A 2024 systematic review and meta-analysis found strong diagnostic performance for several clinician-performed POCUS protocols for DVT, although performance depends on technique, training and the specific protocol used.

    A dedicated review also concluded that POCUS can have excellent diagnostic accuracy for acute proximal lower-extremity DVT when performed by well-trained users, while emphasizing the need for appropriate education and standardized training.

    For a vascular physician evaluating a patient with suspected DVT, this means bedside ultrasound may provide clinically important information immediately.


    2. Compression Ultrasound: A Practical Vascular POCUS Skill

    Compression ultrasound is one of the fundamental skills of venous POCUS.

    The physician identifies the artery and vein in transverse view and applies controlled pressure with the probe.

    The examination may assess selected venous segments according to the protocol being used.

    A vascular POCUS examination may incorporate:

    B-Mode

    for anatomy and compressibility,

    Color Doppler

    for visualization of flow,

    and when appropriate,

    Spectral Doppler

    for additional hemodynamic information.

    Professional ultrasound guidance for peripheral venous examinations emphasizes structured assessment and documentation for complete diagnostic studies.

    This highlights an important distinction:

    Focused DVT POCUS and comprehensive venous duplex ultrasound are related—but they are not always interchangeable.

    If findings are uncertain, symptoms suggest distal or complex disease, or detailed venous mapping is required, a complete vascular duplex examination may still be necessary.


    3. Varicose Veins and Chronic Venous Disease

    Chronic venous disease is a major part of vascular practice.

    Patients may present with:

    • Varicose veins  Point-of-Care Ultrasound (POCUS) in Vascular Medicine & Vascular Surgery
    • Leg heaviness
    • Pain
    • Swelling
    • Skin pigmentation
    • Venous eczema
    • Lipodermatosclerosis
    • Venous ulceration

    Ultrasound plays a fundamental role in evaluating venous anatomy and reflux.

    Current Society for Vascular Surgery, American Venous Forum and American Vein and Lymphatic Society guidelines include duplex ultrasound scanning as a central component in evaluating patients with lower-extremity varicose veins and superficial truncal reflux.

    For the vascular specialist, a handheld ultrasound can be useful during the initial clinical encounter for focused questions.

    For example:

    Which superficial vein is visible beneath the symptomatic area?

    Is the vessel patent?

    What is its approximate diameter and depth?

    Is obvious reflux or abnormal flow suspected?

    However, treatment planning for chronic venous insufficiency generally requires a structured duplex study, including detailed reflux assessment and mapping.

    POCUS can complement that workflow rather than replace it.


    4. Ultrasound-Guided Endovenous Radiofrequency Ablation

    One of the strongest examples of ultrasound becoming an integral part of vascular intervention is Endovenous Radiofrequency Ablation (RFA).

    Endovenous thermal ablation is used in appropriately selected patients with superficial venous reflux and varicose vein disease.

    During a typical ultrasound-guided procedure, ultrasound may assist the physician in:

    Identifying the Target Vein Point-of-Care Ultrasound (POCUS) in Vascular Medicine & Vascular Surgery

    Selecting an Access Site

    Guiding Needle Entry

    Guiding Guidewire and Catheter Position

    Evaluating the Relationship to Deep Veins

    Guiding Tumescent Anaesthesia

    Monitoring the Procedure

    Assessing the Treated Vein After Intervention

    International consensus describes endovenous thermal ablation—including radiofrequency—as a catheter-directed, ultrasound-guided treatment for varicose vein disease.

    A multidisciplinary international position statement also recommends concurrent ultrasound imaging for superficial endovenous procedures including radiofrequency ablation, endovenous laser ablation, cyanoacrylate closure and ultrasound-guided sclerotherapy.

    This makes ultrasound much more than a diagnostic tool for vascular surgeons.

    It becomes a procedural navigation tool.


    5. Ultrasound-Guided Vascular Access

    One of the most practical uses of POCUS is vascular access.

    Every clinician knows the challenge:

    A vein may be palpable in one patient but almost impossible to identify in another.

    Ultrasound allows the operator to visualize:

    Vein

    Artery

    Depth

    Diameter

    Surrounding structures

    Needle

    before and during cannulation.

    POCUS can be used for:

    • Peripheral venous access
    • Central venous access
    • Selected arterial access
    • Difficult vascular access
    • Dialysis access-related procedures

    International evidence-based recommendations support ultrasound guidance for central venous cannulation and note its value in selected peripheral venous and arterial access procedures.

    A review of Cochrane evidence found ultrasound-guided vascular access associated with improvements in outcomes such as first-attempt success and overall success in several studied settings, while also reducing some failed attempts and complications.


    6. Seeing the Needle During Vascular Access

    A major advantage of ultrasound guidance is the ability to observe needle advancement.

    Two commonly used techniques are:

    In-Plane

    The needle advances along the ultrasound imaging plane, potentially allowing visualization of much of the needle shaft and tip.

    Out-of-Plane

    The needle crosses the ultrasound beam and appears as a bright echogenic point when intersecting the imaging plane.

    The important principle is:

    Always understand where the needle tip is.

    Seeing part of the needle does not necessarily mean the operator has identified the tip.

    Training in hand-eye coordination, probe positioning and needle visualization is therefore essential.


    7. Arterial POCUS

    Arterial ultrasound can provide valuable focused information in vascular practice.

    Depending on the clinical situation and device capability, a vascular physician may use ultrasound to evaluate:

    • Arterial location
    • Vessel diameter
    • Patency
    • Pulsatility
    • Calcification
    • Selected flow characteristics
    • Suitable arterial access sites
    • Surrounding anatomy

    Color Doppler can help differentiate arterial and venous flow, while spectral Doppler may provide additional hemodynamic information.

    For comprehensive assessment of Peripheral Arterial Disease (PAD), however, formal vascular testing may involve:

    • Ankle-Brachial Index
    • Segmental pressures
    • Pulse-volume recordings
    • Complete arterial duplex
    • CT angiography
    • MR angiography
    • Conventional angiography

    depending on the clinical situation.

    Therefore:

    POCUS can answer focused arterial questions, but it should not automatically be considered a substitute for comprehensive vascular investigation.


    8. Abdominal Aortic Aneurysm

    The abdominal aorta is another important target for POCUS.

    A focused transabdominal examination can help determine whether the aorta appears enlarged in a patient where an abdominal aortic aneurysm is suspected.

    This may be particularly relevant for patients presenting with combinations such as:

    Abdominal pain

    Back pain

    Hypotension

    Syncope

    and appropriate vascular risk factors.

    Recent evidence continues to support the ability of trained clinicians to detect AAA with POCUS. A 2026 review of systematic reviews reported very high ranges of sensitivity and specificity for clinician-performed POCUS in diagnosing AAA.

    A 2024 systematic review and meta-analysis similarly reported high diagnostic performance in emergency settings.

    For a vascular specialist, however, identifying an aneurysm is only the beginning.

    Detailed treatment planning may require comprehensive ultrasound, CT angiography or other vascular imaging to assess anatomy, branch vessels, morphology and suitability for intervention.


    9. Pseudoaneurysm Assessment

    Pseudoaneurysm can occur following arterial puncture, catheterization, trauma or vascular procedures.

    Ultrasound can help evaluate a suspicious groin or access-site swelling and identify vascular flow patterns suggesting a pseudoaneurysm.

    Depending on the case and operator expertise, ultrasound may also support selected image-guided treatment.

    EFSUMB guidance on ultrasound-guided vascular interventions includes ultrasound for detection of vascular-access complications and ultrasound-guided treatment of arterial pseudoaneurysms.

    This is another example of POCUS moving beyond simple diagnosis into intervention.


    10. Arteriovenous Fistula and Dialysis Access

    Patients receiving haemodialysis depend on reliable vascular access.

    POCUS can be used for focused evaluation of an AV fistula or graft.

    The physician may assess questions such as:

    • Where is the fistula?
    • How deep is the vessel?
    • What is its diameter?
    • Is there visible flow?
    • Is there an obvious abnormality?
    • Where is the most appropriate area for cannulation?

    A review of vascular-access POCUS emphasizes that its goal is often to answer focused bedside questions rather than reproduce a complete fistula or graft duplex examination.

    A broader review found POCUS has been used for AV fistula maturation assessment, identification of abnormalities, difficult cannulation and selection of alternative cannulation sites.

    This distinction perfectly illustrates the philosophy of POCUS:

    Ask a focused question.

    Scan.

    Obtain immediate information.

    Decide whether additional investigation is required.


    11. Color Doppler: Seeing More Than Anatomy

    B-mode ultrasound shows anatomy.

    Color Doppler adds information about blood flow.

    For vascular physicians, this can be particularly valuable.

    Color Doppler may help identify:

    • Vessel flow
    • Flow direction
    • Areas of abnormal flow
    • Relationship between vessels
    • Possible vascular abnormalities
    • Patency during focused assessment

    Spectral Doppler can further provide information about flow velocity and waveform morphology when the equipment and operator training support it.

    For advanced vascular assessment, Doppler capability becomes especially important because vascular medicine is not simply about seeing vessels.

    It is about understanding circulation.


    12. POCUS Before a Vascular Procedure

    Imagine preparing for an intervention.

    Before puncturing the skin, the physician can scan the area and ask:

    Where exactly is the artery?

    Where is the vein?

    How deep is the vessel?

    What is its diameter?

    Is there another vessel nearby?

    Is there calcification?

    Is this the best access point?

    What is the safest needle trajectory?

    This brief pre-procedural scan can transform a landmark-based procedure into an image-informed procedure.

    International vascular-access recommendations support ultrasound screening before cannulation and real-time needle guidance in appropriate settings.


    13. POCUS During the Procedure

    The value continues after skin puncture.

    Real-time ultrasound can potentially allow the operator to see:

    Needle → Vessel → Guidewire → Catheter

    depending on the procedure.

    For endovenous treatment, ultrasound may also be used to observe surrounding anatomy and assist with proper treatment-zone positioning.

    This creates a major difference between:

    “I believe the device is in the correct location.”

    and

    “I can visualize where it is.”


    14. POCUS After the Procedure

    Focused ultrasound may also contribute to immediate post-procedure assessment.

    Depending on the intervention, the physician may look for:

    • Vessel patency
    • Treatment response
    • Hematoma
    • Suspected access-site complication
    • Pseudoaneurysm
    • Local fluid collection
    • Other relevant findings

    More comprehensive post-treatment surveillance may still require a formal vascular duplex study according to the procedure and clinical guideline.

    Duplex ultrasound remains a fundamental part of assessment following many venous interventions.


    POCUS and Endovenous RFA: A Natural Combination

    For a vascular practice performing Radiofrequency Ablation for Varicose Veins, ultrasound and RFA naturally work together.

    A simplified clinical workflow may look like:

    Clinical Assessment

    ↓

    Duplex Evaluation

    ↓

    Treatment Planning

    ↓

    Ultrasound-Guided Venous Access

    ↓

    Catheter Positioning

    ↓

    Tumescent Anaesthesia Under Ultrasound Guidance

    ↓

    Radiofrequency Ablation

    ↓

    Ultrasound Assessment

    Ultrasound provides visualization.

    Radiofrequency provides the therapeutic energy.

    Together, these technologies support modern minimally invasive treatment of appropriately selected superficial venous disease.


    Which Ultrasound Probe Does a Vascular Specialist Need?

    Linear Probe — The Essential Vascular Probe

    For most superficial vascular applications, a high-frequency Linear probe is particularly important.

    It is useful for:

    • DVT assessment
    • Superficial veins
    • Vascular access
    • Carotid and other superficial vessels
    • Varicose veins
    • Endovenous procedures
    • AV fistula
    • Peripheral arteries
    • Needle guidance
    • Soft-tissue assessment

    The rectangular image and high-frequency capability make the linear transducer particularly suitable for superficial anatomy.


    Why a Convex Probe Can Also Be Useful

    Not every vessel is superficial.

    For deeper structures, the Convex probe can provide greater penetration and a wider field of view.

    Potential applications include:

    • Abdominal aorta
    • Iliac-region assessment
    • Deep abdominal structures
    • Selected deep vascular anatomy
    • Abdominal POCUS

    This means that a vascular specialist may benefit from having:

    Linear for superficial vascular imaging

    and

    Convex for deeper abdominal vascular assessment.


    Why Handheld Wireless Ultrasound Makes Sense in Vascular Practice

    Traditional vascular ultrasound systems remain essential for detailed duplex examinations.

    But a vascular surgeon does not perform every clinical assessment inside a vascular laboratory.

    The specialist may be working in:

    • Consultation chamber
    • Vascular clinic
    • Hospital ward
    • Emergency department
    • Procedure room
    • Operating theatre
    • Dialysis unit
    • Bedside
    • Peripheral healthcare facility

    A handheld wireless ultrasound can travel with the physician.

    It can potentially connect to a compatible smartphone or tablet and provide immediate imaging when a focused clinical question arises.

    The workflow becomes:

    Examine → Scan → Visualize → Decide → Intervene when appropriate.

    This is the philosophy behind Point-of-Care Ultrasound.


    SonoHealth Handheld Wireless Ultrasound for Vascular POCUS

    For vascular specialists looking to introduce portable ultrasound into everyday practice, SonoHealth Handheld Wireless Ultrasound provides a practical point-of-care imaging platform.

    Depending on the configuration, it can support:

    Vascular Imaging

    Focused examination of veins and arteries.

    Color Doppler

    Visualization of vascular flow.

    DVT Assessment

    Focused compression ultrasound in appropriately selected patients.

    Vascular Access

    Real-time ultrasound guidance for needle placement.

    Endovenous Procedures

    Support for image-guided vascular intervention.

    AV Fistula Assessment

    Focused evaluation and access guidance.

    Abdominal Vascular Assessment

    With an appropriate deeper-penetration transducer.

    Needle Guidance

    For selected vascular procedures.

    For many vascular applications, the combination of a high-frequency Linear probe + Color Doppler + needle-guidance capability can be particularly useful.

    Adding a Convex probe expands the potential range toward deeper abdominal and aortic imaging.


    POCUS Does Not Replace a Complete Vascular Duplex Study

    This is one of the most important principles when adopting handheld ultrasound.

    A focused POCUS examination and a comprehensive vascular duplex examination are not necessarily the same thing.

    A complete vascular laboratory examination may require:

    • Detailed vessel mapping
    • Standardized Doppler waveforms
    • Velocity measurements
    • Reflux testing
    • Spectral Doppler analysis
    • Multiple standardized anatomical segments
    • Formal interpretation
    • Structured reporting
    • Quality-control protocols

    Professional vascular guidelines continue to rely heavily on comprehensive duplex ultrasound for conditions such as chronic venous disease and treatment planning.

    Therefore, POCUS should be considered:

    A focused clinical tool.

    A procedural guidance tool.

    An extension of vascular examination.

    not automatically a replacement for comprehensive vascular imaging.


    Training Matters

    Ultrasound is operator-dependent.

    A sophisticated ultrasound device is only useful when the physician understands what is being displayed.

    Vascular POCUS training should include:

    • Ultrasound physics
    • Probe orientation
    • Vascular anatomy
    • Artery-versus-vein identification
    • Compression technique
    • B-mode optimization
    • Color Doppler
    • Spectral Doppler where applicable
    • Needle visualization
    • In-plane and out-of-plane approaches
    • Recognition of artifacts
    • Recognition of DVT findings
    • Recognition of vascular-access complications
    • Understanding when comprehensive imaging is required

    Published evidence on DVT POCUS repeatedly emphasizes that good diagnostic performance depends on adequately trained operators.

    Technology + Training + Clinical Knowledge = Effective Vascular POCUS.


    The Future of Vascular Medicine Is Increasingly Visual

    Vascular specialists have always relied heavily on clinical examination.

    They inspect the limb.

    They palpate pulses.

    They evaluate edema.

    They assess skin changes.

    They listen for bruits.

    POCUS adds another dimension:

    They can see the vessel.

    They can see flow.

    They can see the needle.

    They can see the target before intervention.

    This does not replace clinical examination.

    It strengthens it.


    From Palpation to Visualization

    A handheld ultrasound can change the everyday vascular workflow.

    Instead of:

    “I think the vein is here.”

    the physician may be able to say:

    “I can see the vein.”

    Instead of:

    “The vessel should be approximately this deep.”

    “I can measure its depth.”

    Instead of:

    “The needle should be approaching the vessel.”

    “I can follow the needle toward the target.”

    Instead of relying solely on external anatomy:

    The vascular specialist can visualize what lies underneath.

    That is the practical value of POCUS.


    See the Vessel. Understand the Flow. Guide the Procedure.

    Point-of-Care Ultrasound is helping bring real-time vascular imaging closer to the physician and closer to the patient.

    For vascular specialists, its potential spans:

    DVT Assessment

    Venous Examination

    Arterial Assessment

    Vascular Access

    Varicose Vein Procedures

    Endovenous RFA

    AV Fistula Assessment

    Aortic POCUS

    Needle Guidance

    and selected post-procedural assessments.

    The future is not simply about smaller ultrasound machines.

    It is about having relevant imaging available when the clinical decision is being made.


    SonoHealth Handheld Wireless Ultrasound

    Point-of-Care Ultrasound for Modern Vascular Practice

    Vascular Imaging • Color Doppler • DVT Assessment • Vascular Access • Endovenous Procedures • Needle Guidance

    See the Vessel. Understand the Flow. Guide with Precision.

    For vascular surgeons, vascular specialists, hospitals and vascular centers interested in integrating handheld Point-of-Care Ultrasound into clinical practice:

    Unique Medi Trade

    POCUS Solutions • Live Demonstration • Clinical Training Support • Technical Support • Endovenous RFA Solutions

    Contact: +880 1717-811312

    Unique Medi Trade — Advancing Image-Guided Vascular Care in Bangladesh


    Medical Disclaimer

    This article is intended for healthcare-professional education and general information. Point-of-Care Ultrasound should be performed by appropriately trained healthcare professionals within their scope of practice and according to relevant clinical guidelines and institutional protocols.

    Focused POCUS should not replace a comprehensive vascular duplex examination, CT angiography, MR angiography, conventional angiography or specialist vascular imaging when these are clinically indicated. Clinical decisions should be based on the complete patient assessment rather than an isolated POCUS finding.


    SEO Information

    SEO Title:
    Point-of-Care Ultrasound (POCUS) in Vascular Medicine & Vascular Surgery

    Alternative SEO Title:
    POCUS for Vascular Surgeons: DVT, Vascular Access, Varicose Veins & Endovenous Procedures

    Meta Description:
    Discover how Point-of-Care Ultrasound (POCUS) supports vascular specialists in DVT assessment, vascular access, venous and arterial imaging, endovenous RFA, AV fistula assessment and image-guided procedures.

    Suggested URL Slug:
    /point-of-care-ultrasound-pocus-in-vascular-surgery/

    Target Keywords:
    Point-of-Care Ultrasound Vascular, POCUS Vascular Surgery, vascular ultrasound, handheld vascular ultrasound, DVT ultrasound, ultrasound-guided vascular access, varicose vein ultrasound, Endovenous RFA, Color Doppler ultrasound, vascular surgeon ultrasound, SonoHealth Handheld Ultrasound, POCUS Bangladesh

    Suggested Featured Image Text:

    POINT-OF-CARE ULTRASOUND IN VASCULAR MEDICINE

    See the Vessel. Understand the Flow. Guide with Precision.

    SonoHealth Handheld Wireless Ultrasound
  • Point-of-Care Ultrasound (POCUS) in Pain Medicine

    Point-of-Care Ultrasound (POCUS) in Pain Medicine

    Point-of-Care Ultrasound (POCUS) in Pain Medicine: Seeing the Target, Guiding the Needle, Improving Precision

    A New Dimension in Modern Pain Management

    Pain Medicine is becoming increasingly precise, image-guided and minimally invasive.

    Traditionally, many pain procedures were performed using anatomical landmarks, palpation, nerve stimulation, fluoroscopy or CT guidance. Today, Point-of-Care Ultrasound (POCUS) has added another powerful option to the pain physician’s toolkit.

    With ultrasound available directly at the point of care, an appropriately trained pain physician can visualize important structures in real time—including:

    Nerves • Muscles • Fascia • Tendons • Joints • Blood Vessels • Pleura • Bone Surfaces • Needle Path

    This ability to see anatomy while performing an intervention can fundamentally change the way selected pain procedures are planned and performed.

    The American Society of Regional Anesthesia and Pain Medicine (ASRA) describes POCUS as an important skill for regional anesthesiologists and pain physicians and has published expert recommendations regarding its clinical indications and training.

    For the modern pain specialist, ultrasound is therefore becoming more than an imaging machine.

    It can become a visual extension of the clinical examination—and a real-time navigation system for interventions.


    What Is Point-of-Care Ultrasound in Pain Medicine?

    Point-of-Care Ultrasound means performing a focused ultrasound examination at or near the patient’s bedside, consultation room or procedure area to answer a specific clinical question or guide an intervention.

    In Pain Medicine, the physician may ask:Point-of-Care Ultrasound (POCUS) in Internal Medicine

    Where exactly is the target nerve?

    Where is the needle tip?

    Are there blood vessels close to my planned needle path?

    How deep is the target?

    Is the injectate spreading around the intended structure?

    Is there a joint effusion?

    Can I identify the muscle, tendon or fascial plane responsible for the patient’s symptoms?

    Rather than relying only on surface anatomy, ultrasound allows the physician to visualize structures beneath the skin in real time.

    That is one of the major reasons ultrasound guidance has become increasingly important in regional anesthesia and interventional pain practice. Research and expert reviews describe applications ranging from peripheral nerve blocks and fascial-plane procedures to musculoskeletal and chronic pain interventions.


    From Landmark-Guided to Image-Guided Pain Intervention

    Consider a traditional injection performed primarily using anatomical landmarks.

    The physician knows where the nerve or joint should normally be located based on anatomy.

    But every patient is different.

    Body habitus varies.

    Muscle thickness varies.

    Nerve location may vary.

    Blood vessels may be closer to the intended needle trajectory than expected.

    Scar tissue or previous surgery may alter anatomy.

    Ultrasound changes this approach.

    Instead of thinking:

    “The target should be here.”

    The physician may be able to say:

    “I can see the target here.”

    And instead of advancing the needle based primarily on anatomical estimation:

    The physician can potentially visualize the needle approaching the target in real time.

    This is the fundamental advantage of ultrasound-guided pain intervention.


    Why Ultrasound Is Particularly Valuable in Pain Medicine

    Many pain procedures involve relatively small anatomical targets surrounded by structures that physicians would prefer to avoid.

    For example:POINT-OF-CARE ULTRASOUND IN PAIN MEDICINE

    Target nerve

    may be located beside a:

    Blood vessel

    or beneath a:

    Muscle or fascial layer

    or near:

    Pleura

    or another sensitive structure.

    Ultrasound provides real-time anatomical information that can help the trained operator plan a more informed needle trajectory.

    A review of ultrasound-guided chronic pain interventions highlights the ability of ultrasound to visualize the target tissue, surrounding vascular structures and distribution of injected medication.

    This is particularly relevant in procedures where millimeters matter.


    1. Peripheral Nerve Blocks

    Peripheral nerve blocks are among the most important applications of ultrasound in pain medicine.

    Using a high-frequency linear probe, physicians can often identify superficial peripheral nerves and surrounding anatomical structures.

    Depending on indication, training and scope of practice, ultrasound-guided interventions may involve nerves such as:

    • Suprascapular nerve
    • Median nerve
    • Ulnar nerve
    • Radial nerve
    • Greater occipital nerve
    • Lateral femoral cutaneous nerve
    • Ilioinguinal nerve
    • Iliohypogastric nerve
    • Genitofemoral nerve
    • Genicular nerves
    • Selected ankle and foot nerves
    • Other peripheral nerve targets

    A contemporary review of chronic pain interventions describes ultrasound-guided techniques involving many of these peripheral nerve targets.

    The physician can potentially visualize:

    Nerve → Needle → Adjacent vessels → Surrounding tissue → Injectate spread

    during the intervention.


    2. Ultrasound-Guided Diagnostic Nerve Blocks

    Pain Medicine frequently involves answering an important question:

    “Is this structure actually responsible for the patient’s pain?”

    A diagnostic block can sometimes help answer that question.

    For selected conditions, a physician may inject a local anesthetic around a suspected nerve or anatomical target and evaluate the patient’s response.

    Ultrasound can assist with accurate localization of selected peripheral targets.POINT-OF-CARE ULTRASOUND IN PAIN MEDICINE

    This can be valuable because interventional pain management is not simply about treating pain.

    It is also about identifying the pain generator as accurately as possible.

    A carefully performed diagnostic block may therefore become part of the clinical decision-making process before considering longer-lasting interventions.


    3. Ultrasound and Radiofrequency Procedures

    Radiofrequency technology plays an important role in modern interventional Pain Medicine.

    In selected procedures, a physician first identifies the relevant nerve or target structure and then positions a radiofrequency electrode before delivering controlled RF energy.

    Depending on the anatomical target, procedure and physician expertise, ultrasound may assist with target identification and needle/electrode placement.

    Published reviews of ultrasound-guided chronic pain procedures include both diagnostic nerve blocks and radiofrequency-related interventions.

    This creates an important relationship between two technologies:

    Ultrasound helps the physician see.

    Radiofrequency helps the physician treat selected pain targets.

    For a pain practice developing advanced interventional services, these technologies can therefore complement each other in appropriately selected procedures.

    However, not every radiofrequency procedure should be performed using ultrasound alone. Fluoroscopy, CT or other guidance may remain preferred or necessary for certain spinal and deep anatomical targets.


    4. Shoulder Pain

    Shoulder pain is one of the most common musculoskeletal complaints encountered in clinical practice.

    Several structures may potentially contribute to shoulder pain, including:

    • Rotator cuff tendonsPOINT-OF-CARE ULTRASOUND IN PAIN MEDICINE
    • Subacromial-subdeltoid bursa
    • Biceps tendon
    • Acromioclavicular joint
    • Glenohumeral joint
    • Suprascapular nerve
    • Surrounding muscles and soft tissues

    Musculoskeletal ultrasound allows the physician to dynamically assess many superficial shoulder structures.

    For appropriately selected interventions, ultrasound can also guide the needle toward a specific target.

    One important pain intervention is the suprascapular nerve block, which has applications in selected chronic shoulder pain conditions.

    Ultrasound-guided procedures targeting the suprascapular nerve are among techniques described in reviews of chronic pain intervention.


    5. Knee Pain

    Chronic knee pain can result from multiple conditions, including osteoarthritis and other musculoskeletal disorders.

    Ultrasound may assist the physician in evaluating:

    • Joint effusion
    • Superficial tendons
    • Selected ligaments
    • Periarticular soft tissues
    • Baker’s cyst
    • Selected peripheral nerve targets

    Ultrasound can also guide selected knee injections.

    Another increasingly important interventional target in chronic knee pain is the genicular nerve system.

    Ultrasound-guided genicular nerve interventions, including blocks and radiofrequency-related techniques, are described in the pain literature. (PubMed)

    For a physician treating chronic knee pain, ultrasound therefore has potential value across both assessment and intervention.


    6. Hip Pain

    The hip is anatomically deeper than many other musculoskeletal targets, making appropriate probe selection and operator training especially important.

    Ultrasound-guided pain procedures around the hip have continued to develop, and contemporary literature describes ultrasound applications for chronic pain involving the hip, shoulder, knee and lumbar regions. (PubMed)

    Depending on the clinical condition, ultrasound may assist in visualization of selected:

    • TendonsPOINT-OF-CARE ULTRASOUND IN PAIN MEDICINE
    • Muscles
    • Bursae
    • Joint-related structures
    • Peripheral nerves

    For deeper targets, a lower-frequency or convex probe may sometimes be more suitable than a high-frequency linear probe.

    This is why probe selection matters in Pain Medicine.


    7. Myofascial Pain and Trigger-Point Procedures

    Myofascial pain is frequently encountered in Pain Medicine.

    Patients may present with:

    • Localized muscle pain
    • Trigger points
    • Referred pain
    • Muscle spasm
    • Functional limitation

    Trigger-point injections have traditionally often been performed using palpation.

    Ultrasound can provide additional information regarding muscle layers and surrounding anatomy, particularly for deeper targets.

    A systematic review of ultrasound-guided interventions for myofascial trigger points found some evidence supporting ultrasound guidance over blinded interventions, while also emphasizing that the available studies had limitations and further high-quality research is needed. (PubMed)

    This is an important principle in responsible POCUS practice:

    Ultrasound can improve visualization, but clinical outcomes depend on much more than imaging alone.

    Correct diagnosis, patient selection, technique and appropriate treatment strategy remain essential.


    8. Fascial Plane Blocks

    Modern ultrasound has contributed significantly to the development of fascial-plane blocks.

    Rather than always targeting one clearly defined peripheral nerve, the physician may place medication within an anatomical fascial plane where relevant nerves travel.

    Examples described in pain and regional anesthesia literature include:

    • Transversus Abdominis Plane (TAP) blockPOINT-OF-CARE ULTRASOUND IN PAIN MEDICINE
    • Quadratus Lumborum block
    • Rectus sheath block
    • Erector Spinae Plane block
    • Pectoral plane blocks
    • Serratus plane blocks

    Ultrasound allows physicians to identify muscle and fascial layers and observe the spread of injectate within the intended plane.

    Reviews of ultrasound-guided chronic pain interventions include many of these fascial-plane techniques. (PubMed)


    9. Occipital Neuralgia and Headache-Related Pain

    The greater occipital nerve is another potential target in selected pain conditions.

    For patients with appropriate headache syndromes or occipital neuralgia, an ultrasound-guided approach may help the physician identify the relevant anatomical region and nearby structures.

    The greater occipital nerve is among the targets covered in current reviews of ultrasound-guided chronic pain procedures. (PubMed)

    Again, ultrasound does not determine the diagnosis by itself.

    It supports a procedure after the clinician has established an appropriate indication based on history, examination and clinical evaluation.


    10. Ultrasound-Guided Joint Injections

    Joint injections are commonly used in musculoskeletal and pain practice.

    Depending on the condition and physician expertise, ultrasound may be used to guide injections involving selected:

    Shoulder jointsPOINT-OF-CARE ULTRASOUND IN PAIN MEDICINE

    Knee-related structures

    Hip-related structures

    Small peripheral joints

    and periarticular targets.

    The value of imaging guidance is straightforward:

    Identify the anatomy.

    Plan the needle trajectory.

    Observe needle advancement.

    Confirm the intended location.

    This can be particularly useful when anatomy is difficult to identify using surface landmarks alone.


    11. Seeing Blood Vessels Before Advancing the Needle

    One major advantage of ultrasound is the ability to identify vascular structures.

    With B-mode imaging and, where available, Color Doppler, the physician may distinguish blood vessels from surrounding tissues before selecting a needle trajectory.

    This is particularly relevant because some nerves and pain targets lie close to major or small vessels.

    Instead of discovering an unexpected vessel only after advancing the needle, ultrasound may allow the operator to identify it in advance and modify the approach.

    This is one of the reasons real-time imaging can be valuable in interventional Pain Medicine.


    12. Seeing the Needle in Real Time

    Ultrasound-guided procedures are commonly performed using one of two basic approaches:

    In-Plane Technique

    The needle travels along the ultrasound imaging plane, potentially allowing visualization of a substantial portion of the needle shaft and tip.

    Out-of-Plane Technique

    The needle crosses the ultrasound beam and may appear as a bright dot when it intersects the imaging plane.

    Each technique has advantages and limitations.

    What matters most is that the physician understands:

    Probe orientationPOINT-OF-CARE ULTRASOUND IN PAIN MEDICINE

    Target anatomy

    Needle trajectory

    and, critically,

    Needle-tip location.

    A visible needle shaft does not automatically mean that the physician knows where the tip is.

    Training and continuous visualization are therefore essential.


    13. Ultrasound-Guided Injection: Seeing the Drug Spread

    Pain physicians are often interested not only in where the needle ends up but also in where the injected solution spreads.

    Under ultrasound guidance, the physician may observe tissue separation and injectate distribution around the intended nerve or within a fascial plane.

    This provides real-time feedback during selected procedures.

    An ultrasound-guided chronic pain review specifically notes the ability to visualize both targeted tissue and drug distribution, along with nearby vascular anatomy. (PubMed)

    This is something that a landmark-only technique cannot provide.


    14. Ultrasound Without Ionizing Radiation

    Unlike fluoroscopy and CT, diagnostic ultrasound does not use ionizing radiation.

    That can be particularly attractive in pain practices where physicians perform repeated interventions.

    Ultrasound can therefore eliminate radiation exposure for procedures that can appropriately be performed using ultrasound guidance alone.

    Published reviews of chronic pain interventions identify freedom from ionizing radiation as one of ultrasound’s practical advantages compared with fluoroscopy or CT. (PubMed)

    However, this should not lead to the conclusion that ultrasound should replace fluoroscopy for every pain procedure.

    The correct imaging modality depends on the target, procedure, evidence, physician expertise and clinical context.


    Ultrasound vs Fluoroscopy: Not Competitors

    A common mistake is to frame the discussion as:

    Ultrasound OR Fluoroscopy?

    Modern interventional Pain Medicine requires a more sophisticated approach.

    The better question is:

    “Which imaging modality is most appropriate for this particular procedure?”

    Ultrasound is particularly attractive for many:

    • Peripheral nerves
    • MusclesPOINT-OF-CARE ULTRASOUND IN PAIN MEDICINE
    • Tendons
    • Fascial planes
    • Vascular structures
    • Superficial joints
    • Soft-tissue targets

    Fluoroscopy remains extremely important for many:

    • Spinal interventions
    • Epidural procedures
    • Facet-related procedures
    • Deep bony targets
    • Procedures requiring contrast confirmation
    • Other interventions where radiographic landmarks are critical

    In some advanced practices, ultrasound and fluoroscopy may even complement one another.

    The objective is not to choose technology based on convenience.

    The objective is to select the imaging technique that best supports the clinical procedure.


    POCUS Beyond Needle Guidance

    POCUS in Pain Medicine is broader than musculoskeletal injections and nerve blocks.

    ASRA’s expert recommendations describe additional POCUS applications relevant to regional anesthesiologists and pain physicians, including:

    • Lung ultrasound
    • Focused cardiac ultrasound
    • Gastric ultrasound
    • Airway ultrasound
    • Focused assessment in selected acute situations

    (PubMed)

    More recently, ASRA Pain Medicine published expert practice recommendations addressing gastric POCUS for aspiration-risk assessment in medically complex patients undergoing regional anesthesia and pain procedures. (PubMed)

    This demonstrates an important evolution:

    POCUS can help a pain physician assess not only the procedure target, but also selected aspects of the patient’s overall peri-procedural condition.


    Why a Handheld Wireless Ultrasound Is Especially Relevant to Pain Medicine

    Pain physicians frequently work across multiple clinical environments:

    Consultation Chamber

    ↓

    Procedure Room

    ↓

    Operating Theatre

    ↓

    Hospital Bedside

    ↓

    Pain Clinic

    A large ultrasound machine may not always be easily available in each location.

    A handheld wireless ultrasound changes this workflow.

    The ultrasound can potentially travel with the physician.

    Instead of arranging a patient around the ultrasound machine:

    The physician can bring ultrasound to the patient.

    This portability is one reason handheld ultrasound technology is increasingly relevant to point-of-care medicine. ASRA’s POCUS recommendations specifically discuss the impact of handheld ultrasound devices within regional anesthesia and pain practice. (PubMed)


    Why the Linear Probe Is So Important for Pain Physicians

    For many pain procedures, the high-frequency Linear probe is particularly valuable.

    It is commonly suited to relatively superficial structures such as:

    • Peripheral nervesPOINT-OF-CARE ULTRASOUND IN PAIN MEDICINE
    • Tendons
    • Muscles
    • Fascial planes
    • Blood vessels
    • Superficial joints
    • Soft tissues

    High-frequency imaging generally provides better spatial resolution for superficial targets.

    For deeper targets, however, the physician may require a lower-frequency convex probe or another appropriate transducer.

    That is why a versatile pain ultrasound solution may include access to both Linear and Convex imaging capabilities, depending on the procedures being performed.


    SonoHealth Handheld Wireless Ultrasound for Pain Medicine

    For Pain Medicine physicians looking to incorporate ultrasound into daily clinical and interventional workflows, SonoHealth Handheld Wireless Ultrasound provides a portable point-of-care imaging solution.

    The handheld format can support ultrasound use in:

    • Pain clinics
    • Physician chambers
    • Procedure rooms
    • Hospitals
    • Operating rooms
    • Bedside consultations
    • Training and workshops

    For many superficial pain procedures, a Linear probe is particularly important for visualizing nerves, muscles, fascia, vessels and needle trajectory.

    A multi-probe handheld system can further extend the physician’s POCUS capability to deeper structures and broader clinical applications.

    The concept is simple:

    One portable imaging tool, available when the pain physician needs to see beneath the skin.


    POCUS + RFA: A Powerful Combination in Interventional Pain Medicine

    Modern pain practice increasingly combines different technologies.

    For appropriate procedures, the workflow may include:

    Clinical Evaluation

    ↓

    Ultrasound Assessment

    ↓

    Identification of Target

    ↓

    Diagnostic Block

    ↓

    Evaluation of Response

    ↓

    Radiofrequency Intervention When Clinically Indicated

    Ultrasound and Radiofrequency Ablation therefore have complementary roles in selected pain-management pathways.

    Unique Medi Trade works with pain physicians in Bangladesh across both Point-of-Care Ultrasound and Radiofrequency Pain Management technologies, creating an opportunity to support integrated interventional pain practices with imaging, RF technology, technical support and clinical education.


    The Ultrasound Machine Alone Is Not Enough

    POCUS is highly operator-dependent.

    Simply purchasing an ultrasound device does not automatically make an intervention more accurate or safer.

    Physicians require knowledge and hands-on training in:

    • Ultrasound physics
    • Probe handling
    • Sonoanatomy
    • Image optimization
    • Needle visualization
    • In-plane technique
    • Out-of-plane technique
    • Doppler
    • Recognition of artifacts
    • Sterile technique
    • Procedure-specific anatomy
    • Recognition of limitations

    ASRA’s expert recommendations emphasize the importance of structured POCUS education and training for regional anesthesiologists and pain physicians. (PubMed)

    Technology therefore represents only one part of the equation.

    Technology + Training + Anatomy + Technique + Clinical Judgment = Effective POCUS Practice


    Does Ultrasound Make Every Pain Procedure Better?

    Not necessarily.

    This is an important clinical distinction.

    Evidence supporting ultrasound varies according to the procedure.

    A systematic review comparing ultrasound-guided approaches with traditional guidance techniques in chronic pain found that ultrasound could match or improve some performance and safety-related outcomes, but the available evidence was insufficient to conclude that ultrasound improved long-term pain-relief efficacy across procedures. (PubMed)

    This reinforces an important principle:

    Better visualization does not automatically guarantee a better clinical outcome.

    Patient selection, diagnosis, procedural technique and treatment strategy remain fundamental.

    POCUS should therefore be used where clinically appropriate—not simply because ultrasound is available.


    The Future of Pain Medicine Is More Visual

    Pain physicians work in a specialty where anatomical precision is critical.

    The therapeutic target may be:

    A nerve only a few millimeters wide.

    The safe needle pathway may pass between:

    Muscle, fascia and blood vessels.

    The treatment may require the physician to know exactly:

    Where the needle tip is.

    This is where Point-of-Care Ultrasound has the potential to transform the procedural experience.

    The physician does not have to rely solely on what can be felt from the surface.

    The physician can look beneath it.


    See the Anatomy. See the Needle. Treat with Precision.

    For a modern Pain Medicine practice, POCUS can support the transition from:

    Landmark-Based Intervention

    to

    Image-Guided Intervention

    and from:

    Anatomical Estimation

    to

    Real-Time Visualization.

    Whether the physician is evaluating a peripheral nerve, performing a diagnostic block, planning an injection or integrating ultrasound into selected radiofrequency procedures, the fundamental advantage remains the same:

    See what you are targeting.

    See what you want to avoid.

    See where your needle is going.

    That is the real value of ultrasound in interventional Pain Medicine.


    SonoHealth Handheld Wireless Ultrasound

    Point-of-Care Ultrasound for Modern Pain Medicine

    Nerve Visualization • Musculoskeletal Imaging • Ultrasound-Guided Injection • Needle Guidance • Interventional Pain Procedures

    See the Target. Guide the Needle. Treat with Precision.

    For physicians, pain clinics and hospitals interested in incorporating Point-of-Care Ultrasound into their Pain Medicine practice:

    Unique Medi Trade

    POCUS Solutions • Live Demonstration • Physician Training Support • Technical Support • RFA Pain Management Solutions

    Contact: +880 1717-811312

    Unique Medi Trade — Advancing Image-Guided Pain Medicine in Bangladesh


    Medical Disclaimer

    This article is intended for healthcare-professional education and general information. Ultrasound-guided pain procedures should only be performed by appropriately trained and credentialed healthcare professionals within their scope of practice and according to relevant clinical guidelines and institutional protocols.

    Point-of-Care Ultrasound does not replace fluoroscopy, CT, MRI, comprehensive diagnostic ultrasound or specialist imaging when these are clinically indicated. Selection of imaging guidance should depend on the procedure, anatomical target, available evidence, patient condition and physician expertise.


  • Point-of-Care Ultrasound (POCUS) in Internal Medicine

    Point-of-Care Ultrasound (POCUS) in Internal Medicine

    Point-of-Care Ultrasound (POCUS) in Internal Medicine: Bringing Real-Time Imaging to the Bedside

    From “What Do I Think?” to “What Can I See?”

    For generations, Internal Medicine physicians have depended on four fundamental tools at the bedside:

    History → Inspection → Palpation → Auscultation

    Today, another powerful tool is becoming increasingly relevant:

    Point-of-Care Ultrasound — POCUS.Point-of-Care Ultrasound (POCUS) in Internal Medicine

    POCUS enables appropriately trained physicians to perform focused ultrasound examinations at the patient’s bedside and integrate real-time imaging findings with the history, physical examination and other clinical information.

    For an Internal Medicine physician managing patients with shortness of breath, hypotension, edema, acute kidney injury, chest pain, heart failure, pleural effusion or unexplained abdominal distension, immediate ultrasound information can help answer focused clinical questions without always waiting for conventional imaging.

    The American College of Physicians formally recognizes the important role of POCUS in Internal Medicine and notes its increasing use among internists and subspecialists to improve the timeliness and accuracy of diagnosis.

    The European Federation of Internal Medicine has similarly described POCUS as a useful tool for internists across emergency departments, hospital wards, consultations and even home-care settings.

    What Is Point-of-Care Ultrasound?

    Point-of-Care Ultrasound is a focused ultrasound examination performed and interpreted by the treating clinician at or near the point of patient care.

    The key word is focused.

    POCUS is usually not intended to reproduce an entire comprehensive echocardiogram, abdominal ultrasound or radiology examination.

    Instead, it is commonly used to answer specific clinical questions.

    For example:

    Does this breathless patient have B-lines?

    Is there a pleural effusion?

    Is a pericardial effusion visible?

    Does gross left ventricular systolic function appear significantly reduced?

    Is free fluid present in the abdomen?

    Is urinary retention contributing to acute kidney injury?Point-of-Care Ultrasound (POCUS) in Internal Medicine

    Is hydronephrosis visible?

    Could proximal deep-vein thrombosis be present?

    Where is the safest site for thoracentesis or paracentesis?

    This question-oriented approach makes POCUS especially relevant to Internal Medicine.

    A 2025 consensus process involving Internal Medicine POCUS experts identified 12 core diagnostic indications and six procedural indications, with applications including focused cardiac, gallbladder and urinary bladder ultrasound.


    Why POCUS Matters in Internal Medicine

    Internists frequently manage patients whose symptoms can originate from several organ systems simultaneously.

    Consider a common presentation:

    A 68-year-old patient presents with severe shortness of breath.

    The differential diagnosis could include:

    • Acute heart failure
    • Pneumonia
    • Pleural effusion
    • Pneumothorax
    • Pulmonary embolism
    • COPD or asthma exacerbation
    • Pericardial disease
    • Other cardiopulmonary conditions

    History, physical examination, ECG, laboratory investigations and formal imaging remain important.

    But bedside ultrasound may provide additional information within minutes.

    This ability to integrate ultrasound findings immediately into clinical reasoning is one of the major advantages of POCUS.

    A 2025 Australian and New Zealand Internal Medicine consensus statement endorsed POCUS in clinical scenarios including fluid-status assessment, undifferentiated shock or hypotension, dyspnea/respiratory failure, acute kidney injury, suspected venous thromboembolism, joint effusion, invasive procedures and guidance of diuretic therapy in heart failure.


    1. Lung Ultrasound in Shortness of Breath

    Dyspnea is one of the most frequent and challenging presentations in Internal Medicine.

    A patient with acute breathing difficulty may have a cardiac, pulmonary or systemic cause.

    With lung POCUS, a trained physician can evaluate findings such as:

    • Lung sliding
    • B-lines
    • Pleural effusion
    • Lung consolidation patterns
    • Findings suggestive of pneumothorax

    International evidence-based recommendations on point-of-care lung ultrasound were updated in 2026, reflecting the growing body of evidence and increasingly established role of lung ultrasound in clinical practice.

    B-Lines

    Multiple B-lines may be seen in conditions associated with increased extravascular lung water, although they are not specific to one disease.

    For an Internal Medicine physician managing a patient with suspected heart failure, lung ultrasound findings can be interpreted together with:

    Symptoms + Physical examination + Cardiac POCUS + IVC assessment + Laboratory findings + Other imaging

    This multi-organ approach can provide a much richer clinical picture than relying on a single finding alone.


    2. POCUS in Heart Failure

    Heart failure is another major area where POCUS can be useful.

    Patients may present with:

    • Dyspnea
    • Orthopnea
    • Peripheral edema
    • Fatigue
    • Raised JVP
    • Pulmonary congestion
    • Hypotension

    A focused bedside examination may allow the trained internist to assess several complementary areas.

    Lung

    Are B-lines present?

    Is there a pleural effusion?Point-of-Care Ultrasound (POCUS) in Internal Medicine

    Heart

    Does gross left ventricular systolic function appear preserved or significantly reduced?

    Is pericardial fluid visible?

    Are there findings that raise concern for right ventricular abnormality?

    Inferior Vena Cava

    What does the IVC look like in the context of the entire clinical assessment?

    Used appropriately, these observations can contribute to assessment of congestion and hemodynamic status.

    The 2025 Internal Medicine Society of Australia and New Zealand consensus specifically supported POCUS for fluid-status assessment and guidance of diuretic therapy in heart failure.

    Importantly, focused cardiac ultrasound is not equivalent to comprehensive echocardiography.

    When detailed valve assessment, chamber quantification, Doppler measurements or other advanced evaluation is required, formal echocardiography remains essential.


    3. Focused Cardiac Ultrasound

    The heart is one of the most important POCUS targets in acute Internal Medicine.

    Depending on training and clinical context, focused cardiac ultrasound may help answer questions such as:

    • Is there a significant pericardial effusion?
    • Does global LV systolic function appear markedly reduced?Point-of-Care Ultrasound (POCUS) in Internal Medicine
    • Is there obvious right ventricular enlargement?
    • Is the heart hyperdynamic in an appropriate clinical context?
    • Are there findings that may help explain shock or dyspnea?

    Internal Medicine POCUS literature includes focused cardiac examination among core domains, and current training consensus frameworks include cardiac ultrasound skills alongside lung, abdominal, procedural and vascular applications.

    The objective is not:

    “Perform a complete cardiology echocardiogram.”

    The objective is:

    “Answer a focused bedside question that may change immediate clinical management.”


    4. POCUS in Undifferentiated Shock and Hypotension

    Few clinical situations require faster decision-making than a patient with hypotension or shock.

    Possible causes may include:

    • HypovolemiaPoint-of-Care Ultrasound (POCUS) in Internal Medicine
    • Sepsis
    • Cardiogenic shock
    • Obstructive processes
    • Hemorrhage
    • Mixed etiologies

    POCUS can be particularly powerful in these situations because the physician can evaluate several organ systems rapidly.

    A focused examination may include:

    Heart

    Gross ventricular function and pericardial fluid.

    Lungs

    B-lines, pleural findings or pneumothorax patterns.

    IVC

    Interpreted carefully within the broader hemodynamic context.

    Abdomen

    Free fluid where clinically relevant.

    Vascular System

    Selected venous assessment when thromboembolic disease is suspected.

    Undifferentiated shock or hypotension is among the clinical scenarios specifically supported in the 2025 Internal Medicine consensus statement.

    This illustrates one of the greatest strengths of POCUS:

    One device can provide focused information from multiple organ systems during the same bedside assessment.


    5. Inferior Vena Cava and Volume Assessment

    The inferior vena cava, or IVC, is commonly incorporated into bedside ultrasound assessment.

    An internist may examine:Point-of-Care Ultrasound (POCUS) in Internal Medicine

    • IVC size
    • Respiratory variation
    • The overall clinical context

    However, IVC findings should not be interpreted in isolation as a simple measurement of whether a patient is “dry” or “fluid overloaded.”

    Mechanical ventilation, right-sided cardiac pressures, respiratory effort and several other factors can influence IVC appearance.

    The best use of POCUS is therefore integrative.

    Physical examination

    Lung ultrasound

    Cardiac findings

    IVC findings

    Clinical history

    Laboratory and other diagnostic information

    This combined approach is much more powerful than relying on one ultrasound measurement alone.


    6. Pleural Effusion

    Pleural effusion is frequently encountered in Internal Medicine.

    It may occur in association with:

    • Heart failure
    • Infection
    • Malignancy
    • Liver disease
    • Renal disease
    • Other systemic conditions

    Bedside ultrasound can help identify pleural fluid and provide information about its location and approximate extent.

    It can also be used to guide thoracentesis when the procedure is clinically indicated and performed by an appropriately trained physician.

    The Society of Hospital Medicine has published recommendations related to POCUS for bedside procedures including thoracentesis, paracentesis, vascular access and lumbar puncture.

    This is an important distinction:

    POCUS is not only a diagnostic tool.

    It can also be a procedural guidance tool.


    7. Pneumothorax Assessment

    Pneumothorax may require rapid recognition, particularly in critically ill or deteriorating patients.

    Lung ultrasound can evaluate specific sonographic findings associated with pneumothorax.

    Because the examination can be performed immediately at the bedside and repeated when clinically necessary, POCUS may be particularly useful in acute-care environments.

    However, sonographic findings must be interpreted by trained operators and integrated with the patient’s clinical status and other investigations.


    8. Pneumonia and Lung Consolidation

    Lung POCUS may also identify peripheral consolidation patterns and associated pleural abnormalities.

    For an Internal Medicine physician evaluating:

    Fever + Cough + Dyspnea + Hypoxia

    POCUS findings can become another component of the diagnostic assessment.

    It does not eliminate the need for chest radiography, CT, microbiology or other investigations when clinically indicated.

    Instead, it gives the treating physician another source of real-time bedside information.


    9. POCUS in Acute Kidney Injury

    Acute kidney injury is a common problem in hospitalized medical patients.

    The causes may be:

    Pre-renal → Renal → Post-renal

    POCUS can contribute particularly to selected questions related to urinary obstruction and bladder volume.

    A physician may assess:

    • Kidney appearance
    • Possible hydronephrosis
    • Urinary bladder volume
    • Urinary retention

    Current Internal Medicine consensus recommendations include acute kidney injury among clinical scenarios where POCUS can provide benefit, with abdominal applications including relevant renal and urinary assessment.

    Imagine a patient whose creatinine is rapidly rising.

    Instead of relying only on laboratory values and physical examination, focused bedside imaging may help the clinician determine whether an obvious obstructive process requires further investigation.


    10. Bladder Assessment

    Portable ultrasound can be particularly practical when urinary retention is suspected.

    Focused bladder imaging may help estimate whether the bladder is distended and may contribute to decisions about catheterization or further urological evaluation.

    The 2025 U.S. Internal Medicine residency POCUS consensus specifically included urinary bladder ultrasound and bladder-volume assessment within its recommended applications and skills.


    11. Abdominal Free Fluid and Ascites

    Patients with chronic liver disease, heart failure, malignancy and other medical conditions may develop ascites.

    POCUS can help determine:

    • Whether free abdominal fluid is visible
    • Where fluid pockets are located
    • Whether there may be a suitable site for a procedure

    For patients requiring paracentesis, ultrasound can also assist in selecting a safer entry site.

    Earlier Canadian Internal Medicine ultrasound consensus recommendations included abdominal free fluid as a core POCUS application and ultrasound-guided paracentesis among core procedural skills.


    12. Gallbladder Assessment

    Depending on training and institutional scope, abdominal POCUS may also be used for focused gallbladder assessment.

    For a patient presenting with:

    Right upper abdominal pain + Fever + Nausea

    POCUS may provide additional information regarding gallstones or gallbladder abnormalities.

    A comprehensive abdominal ultrasound or other diagnostic imaging may still be required depending on the clinical picture.

    The value of POCUS is that focused information may be available during the initial patient assessment.


    13. Deep Vein Thrombosis

    A patient presents with:

    Unilateral leg swelling + Pain + Clinical suspicion of DVT

    Compression ultrasound performed by an appropriately trained physician can help assess selected proximal veins for suspected deep-vein thrombosis.

    Evaluation for suspected venous thromboembolism is included among endorsed Internal Medicine POCUS clinical scenarios in contemporary consensus recommendations.

    A review of Internal Medicine POCUS applications also highlights examination of major venous trunks for proximal venous thrombosis.

    Depending on the circumstances, comprehensive vascular ultrasound or additional investigation may still be required.


    14. Ultrasound-Guided Procedures

    One of the most established roles of bedside ultrasound is procedural guidance.

    Internal Medicine physicians may perform procedures such as:

    • Thoracentesis
    • Paracentesis
    • Central venous access
    • Peripheral vascular access
    • Selected joint procedures
    • Other bedside interventions

    Ultrasound allows the physician to visualize anatomy before—or in some cases during—the procedure.

    For example, before thoracentesis the physician can identify:

    Chest wall → Pleural space → Fluid → Lung

    Before paracentesis:

    Abdominal wall → Peritoneal fluid → Adjacent structures

    For vascular access:

    Vein → Artery → Surrounding structures → Needle path

    The Society of Hospital Medicine emphasizes POCUS for both answering specific diagnostic questions and guiding invasive bedside procedures.


    POCUS Changes the Traditional Bedside Workflow

    Consider the traditional model:

    Patient Examination

    ↓

    Ultrasound Requested

    ↓

    Patient Transferred to Imaging Department

    ↓

    Examination Performed

    ↓

    Report Prepared

    ↓

    Physician Reviews Result

    This process remains necessary for many comprehensive diagnostic examinations.

    But POCUS creates another pathway for appropriately selected clinical questions:

    Patient Examination

    ↓

    Focused Bedside Ultrasound

    ↓

    Immediate Integration with Clinical Findings

    ↓

    Clinical Decision

    The advantage is not simply speed.

    It is the ability to correlate imaging with what the physician is observing at that exact moment.


    POCUS Is the Visual Extension of the Physical Examination

    Consider how medical examination has evolved.

    A physician can:

    Listen to the heart with a stethoscope.

    POCUS may allow the trained physician to look at gross cardiac function.

    A physician can:

    Listen to the lungs.

    POCUS may allow the physician to evaluate for B-lines, pleural fluid or selected lung abnormalities.

    A physician can:

    Examine peripheral edema and estimate the JVP.

    POCUS can provide additional information from the lungs, heart and venous system.

    A physician can:

    Palpate the abdomen.

    POCUS may help visualize ascites, bladder distension, gallbladder findings or selected renal abnormalities.

    POCUS should therefore not be viewed simply as a smaller version of a radiology ultrasound machine.

    For the trained internist, it can become a visual extension of bedside clinical examination.


    The Power of Multi-Organ POCUS

    One of the greatest advantages of POCUS in Internal Medicine is the ability to combine information from multiple organs.

    For example, consider a patient presenting with acute dyspnea.

    Instead of asking only:

    “What do the lungs show?”

    The physician may evaluate:

    Lungs

    B-lines? Pleural effusion? Consolidation? Pneumothorax pattern?

    Heart

    Gross LV function? Pericardial effusion? Right-heart abnormalities?

    IVC

    What does venous filling look like within the overall context?

    Veins

    Is DVT assessment indicated?

    This concept of integrated multi-organ ultrasound fits particularly well with Internal Medicine because internists are trained to treat the patient as a whole rather than focusing exclusively on one organ.


    Why Handheld Wireless Ultrasound Is Important for POCUS

    POCUS becomes particularly practical when the ultrasound system can move with the physician.

    Traditional ultrasound machines can provide sophisticated imaging capabilities, but they may be large, expensive and located in designated departments.

    A handheld wireless ultrasound can make ultrasound accessible in:

    • Medicine wards
    • Doctor’s chambers
    • Emergency rooms
    • ICU/HDU
    • Outpatient departments
    • Rural hospitals
    • Mobile medical services
    • Bedside rounds

    The physician can potentially carry the device from one patient to another and connect it to a compatible smartphone or tablet.

    This portability represents a fundamental change in ultrasound workflow.

    Ultrasound no longer has to be a place the patient goes.

    It can become a tool that comes to the patient.


    SonoHealth Handheld Wireless Ultrasound for Internal Medicine POCUS

    For Internal Medicine physicians interested in incorporating POCUS into clinical practice, SonoHealth Handheld Wireless Ultrasound offers a portable approach to point-of-care imaging.
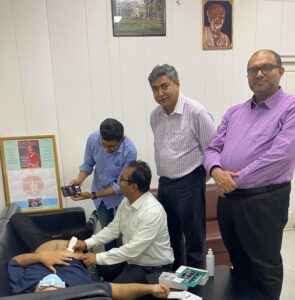
    Depending on the probe configuration, handheld ultrasound can support applications involving:

    Convex Probe

    Useful for deeper structures and abdominal applications such as:

    • Liver
    • Gallbladder
    • Kidneys
    • Urinary bladder
    • Ascites
    • IVC
    • General abdominal assessment

    Phased/Cardiac Probe

    Useful for focused cardiac and thoracic applications such as:

    • Focused cardiac assessment
    • Pericardial effusion
    • Gross ventricular function
    • Pleural assessment
    • Lung POCUS

    Linear Probe

    Useful for superficial and vascular applications including:

    • Vascular access
    • DVT assessment
    • Pleural and superficial structures
    • Soft tissue
    • Selected musculoskeletal applications

    A 3-in-1 handheld ultrasound configuration combining Linear + Convex + Cardiac/Phased capabilities can therefore be particularly practical for physicians who want one portable device for multi-organ POCUS.


    One Device. Multiple Clinical Questions.

    For an Internal Medicine physician, a versatile handheld POCUS system can potentially support focused assessment from:

    Heart

    ↓

    Lung

    ↓

    IVC

    ↓

    Abdomen

    ↓

    Kidney & Bladder

    ↓

    Peripheral Veins

    ↓

    Procedural Guidance

    This is why POCUS is particularly well aligned with Internal Medicine.

    The specialty itself is multi-system.

    The ultrasound tool should be equally versatile.


    POCUS Does Not Replace Comprehensive Diagnostic Ultrasound

    This is an essential principle.

    Point-of-Care Ultrasound should not be presented as a replacement for radiologists, cardiologists, sonologists or comprehensive diagnostic ultrasound examinations.

    POCUS generally answers a focused clinical question.

    A comprehensive examination may require:

    • Detailed imaging protocol
    • Advanced Doppler analysis
    • Multiple standardized measurements
    • Formal echocardiography
    • Detailed organ evaluation
    • Specialist interpretation
    • Structured reporting
    • CT, MRI or other imaging when indicated

    Professional ultrasound standards emphasize appropriate indications, operator competence, structured examinations, reporting and quality management.

    POCUS should complement existing diagnostic pathways—not compete with them.


    Training Is More Important Than the Machine

    Owning an ultrasound device does not automatically make someone competent in POCUS.

    Successful implementation requires:

    Ultrasound Knowledge

    Hands-On Training

    Supervised Scanning

    Image Interpretation

    Clinical Integration

    Recognition of Limitations

    Structured training is strongly emphasized by professional organizations.

    The European Federation of Internal Medicine recommends development of structured POCUS training, while the American College of Physicians provides dedicated foundational and practical POCUS training programs for Internal Medicine physicians.

    The Society of Hospital Medicine similarly provides POCUS education and competency-focused training pathways for hospitalists.

    The future of POCUS therefore depends on two things:

    Better technology.

    and

    Better-trained physicians.


    POCUS and the Future of Internal Medicine

    The stethoscope transformed clinical examination approximately two centuries ago.

    Today, handheld ultrasound is creating another important evolution in bedside medicine.

    The goal is not to replace the stethoscope.

    The goal is not to replace radiology.

    The goal is not to replace echocardiography.

    The goal is to give the physician more clinical information at the point of care.

    International professional organizations are increasingly incorporating POCUS into Internal Medicine practice and education. The ACP formally supports its role in Internal Medicine, the Society of Hospital Medicine has developed position statements and training pathways, and recent consensus recommendations have defined increasingly detailed core applications for Internal Medicine physicians.

    For the modern internist, the question may therefore be changing from:

    “Why should I learn POCUS?”

    to:

    “How should I integrate POCUS safely and effectively into my clinical practice?”


    See More at the Bedside. Decide with More Information.

    Internal Medicine is built around clinical reasoning.

    POCUS adds real-time visualization to that process.

    When used by appropriately trained physicians, it can support focused assessment of the:

    Heart • Lungs • IVC • Abdomen • Kidneys • Bladder • Peripheral Veins

    and provide ultrasound guidance for selected bedside procedures.

    The result is not simply a new piece of equipment.

    It is a different way of approaching bedside medicine.

    Listen. Examine. Visualize. Integrate. Decide.


    SonoHealth Handheld Wireless Ultrasound

    Point-of-Care Ultrasound for Modern Internal Medicine

    Portable. Wireless. Multi-Organ Imaging.

    See More. Diagnose Faster. Treat Better.

    For physicians, hospitals and institutions interested in introducing or expanding a Point-of-Care Ultrasound program:

    Unique Medi Trade

    Clinical Demonstration • POCUS Solutions • Technical Support • Training Support

    Contact: +880 1717-811312


    Medical Disclaimer

    This article is intended for healthcare-professional education and general information. Point-of-Care Ultrasound should be performed by appropriately trained clinicians within their scope of practice and according to relevant institutional protocols and professional standards. POCUS findings should always be interpreted together with the patient’s clinical history, examination and other investigations. Focused POCUS does not replace comprehensive diagnostic ultrasound, echocardiography, radiology assessment or specialist evaluation when these are clinically indicated.

  • Point-of-Care Ultrasound in Obstetrics & Gynaecology

    Point-of-Care Ultrasound in Obstetrics & Gynaecology

    Point-of-Care Ultrasound in Obstetrics & Gynaecology: Why TVS + Convex Ultrasound Is a Powerful Combination

    Bringing Ultrasound Closer to the Patient

    Ultrasound has always been central to Obstetrics and Gynaecology. What is changing today is where, when and how ultrasound is being used.

    With the development of portable and handheld ultrasound technology, an OB/Gynae physician no longer has to think of ultrasound only as a separate investigation performed in a dedicated imaging room.

    Point-of-Care Ultrasound (POCUS) brings real-time imaging directly to the consultation room, bedside, emergency department, labour ward or clinic.

    For an Obstetrician and Gynaecologist, one particularly practical configuration is a combination of:

    TVS — Transvaginal Ultrasound

    and

    Convex — Transabdominal Ultrasound

    Together, these two scanning approaches can support a wide range of focused obstetric and gynaecological assessments throughout different stages of a woman’s care.

    International guidance increasingly recognizes the role of POCUS in Obstetrics and Gynaecology. In 2025, the International Society of Ultrasound in Obstetrics and Gynecology (ISUOG) published dedicated practice guidelines addressing appropriate use of POCUS in Ob/Gyn clinical scenarios, particularly when immediate bedside sonographic evaluation can assist patient management.


    What Is Point-of-Care Ultrasound?

    Point-of-Care Ultrasound is a focused ultrasound examination performed by the treating healthcare professional at or near the point of patient care.

    Instead of sending every patient away for imaging before making the next clinical decision, a trained physician can use POCUS as an extension of the clinical examination.Point-of-Care Ultrasound for OB/Gynae

    For example, a patient may present with:

    • Early pregnancy with lower abdominal pain
    • Vaginal bleeding
    • Uncertain gestational age
    • Pelvic pain
    • Suspected pelvic mass
    • Need to confirm fetal presentation
    • Need for a rapid assessment of fetal cardiac activity
    • Concern about fluid or another clinically relevant finding

    A focused ultrasound examination may provide immediate additional information that helps the clinician determine the appropriate next step.

    POCUS has particular value because real-time sonographic findings can immediately be interpreted alongside the patient’s symptoms, examination and clinical history.


    Why OB/Gynae Needs Both TVS and Convex Ultrasound

    There is no single ultrasound approach that is ideal for every Obstetric and Gynaecological patient.

    This is why having both Transvaginal and Transabdominal ultrasound capability can be valuable.

    The American College of Obstetricians and Gynecologists (ACOG) describes both approaches as standard ways of performing pelvic ultrasound. The appropriate approach depends on the structures that need to be visualized and the clinical reason for the examination.Point-of-Care Ultrasound for OB/Gynae

    TVS — Closer Imaging for Pelvic and Early Pregnancy Assessment

    A transvaginal probe can provide high-resolution imaging of structures within the pelvis because the transducer is positioned relatively close to the uterus, endometrium, cervix and adnexa.

    TVS is particularly valuable when clinicians require a closer view of pelvic anatomy.

    It can support assessment of areas such as:

    • Uterus
    • Endometrium
    • Cervix
    • Ovaries
    • Adnexal regions
    • Early intrauterine pregnancy
    • Early fetal structures
    • Pelvic masses
    • Selected fertility-related assessments

    Convex — A Broader Transabdominal View

    A convex probe is placed over the abdomen and provides a broader field of view with deeper penetration.

    This makes it useful across multiple phases of obstetric assessment and for broader pelvic imaging.

    Depending on gestational age, clinical indication and physician training, the convex probe may support focused evaluation of:

    • Pregnancy location and general overviewPoint-of-Care Ultrasound for OB/Gynae
    • Fetal presence and cardiac activity
    • Fetal position or presentation
    • Fetal movement
    • Basic fetal measurements where appropriate
    • Placental location
    • Amniotic fluid assessment
    • Uterine overview
    • Larger pelvic structures
    • Abdominal and pelvic assessment

    Together, TVS + Convex creates a versatile ultrasound toolkit for the OB/Gynae physician.


    1. POCUS in Early Pregnancy

    Early pregnancy is one of the situations in which rapid access to ultrasound can be particularly useful.

    A woman may come to an OB/Gynae clinic with:

    “My pregnancy test is positive, but I have pain.”

    or

    “I am pregnant and experiencing bleeding.”

    These presentations may require timely assessment.

    A trained clinician may use focused ultrasound to obtain information relevant to questions such as:Point-of-Care Ultrasound for OB/Gynae

    • Is an intrauterine gestational sac visualized?
    • Is an embryo visualized when expected?
    • Is fetal cardiac activity identified?
    • Are there concerning adnexal findings?
    • Is there free pelvic fluid?
    • Does the clinical picture require urgent referral or comprehensive imaging?

    ACOG notes that ultrasound is used during pregnancy for several purposes, including assessment of fetal health and development and evaluation when ectopic pregnancy is a concern.

    In early pregnancy, the TVS probe can be especially important because of the proximity of the transducer to the pelvic organs.


    2. Pelvic Pain: Seeing While Evaluating

    Pelvic pain can have multiple possible causes.

    History and physical examination remain fundamental, but immediate ultrasound information may help the treating physician refine the clinical picture.

    A focused TVS examination can provide information about the:

    Uterus → Endometrium → Ovaries → Adnexa → Pelvic cavity

    It may reveal findings that require further investigation or formal imaging.Point-of-Care Ultrasound for OB/Gynae

    Ultrasound is commonly used in women’s healthcare to evaluate pelvic pain and pelvic masses such as ovarian cysts or uterine fibroids.

    The clinical advantage of POCUS is not that it replaces every comprehensive ultrasound examination.

    The advantage is that the physician can potentially obtain clinically useful information immediately.


    3. Abnormal Uterine Bleeding

    Abnormal uterine bleeding is another common reason women visit a Gynaecologist.

    In appropriate patients, transvaginal ultrasound can assist in evaluating the uterus and endometrium as part of the overall clinical work-up.

    Depending on the clinical situation, ultrasound may provide information relating to:

    • Endometrial appearance
    • Uterine morphology
    • Fibroids
    • Other structural abnormalities
    • Ovarian or adnexal findings

    ISUOG’s 2026 consensus guidance specifically addresses sonographic assessment of the endometrium and standardized approaches to performing and reporting gynecological ultrasound examinations.

    POCUS findings should always be interpreted within the complete clinical context, with formal diagnostic imaging or additional investigation arranged when necessary.


    4. Fibroids and Other Uterine Findings

    Uterine fibroids are frequently encountered in Gynaecology.

    Ultrasound can help physicians assess the uterus and identify findings compatible with fibroids.

    TVS may provide close pelvic visualization, while a convex abdominal probe can offer a broader view—particularly when the uterus is enlarged or a wider field is required.

    This demonstrates one of the key advantages of having both TVS and Convex capability in the same portable ultrasound platform.

    The clinician can choose the scanning approach according to the patient and the clinical question.


    5. Ovarian and Adnexal Assessment

    The ovaries and adnexa represent another major area of gynaecological ultrasound.

    TVS can help visualize ovarian morphology and identify adnexal abnormalities requiring further evaluation.

    Ultrasound may be used to evaluate:

    • Ovarian cysts
    • Adnexal masses
    • Pelvic pain
    • Selected infertility-related questions
    • Other pelvic abnormalities

    ACOG identifies pelvic masses, infertility evaluation and monitoring of infertility treatment among the established uses of ultrasound in women’s healthcare.

    Complex ovarian or adnexal lesions, however, may require a comprehensive specialist ultrasound examination, Doppler assessment and/or further imaging rather than relying on a limited POCUS examination alone.


    6. Fetal Cardiac Activity at the Point of Care

    One of the most clinically meaningful moments in obstetric practice is confirming fetal cardiac activity.

    Depending on gestational age, a physician may use TVS or transabdominal imaging to evaluate fetal cardiac activity.

    For patients presenting with pain, bleeding or pregnancy-related anxiety, being able to perform an appropriate focused scan during the clinical encounter may provide valuable immediate information.

    It can also help clinicians decide whether further formal evaluation is required.


    7. Fetal Presentation

    As pregnancy progresses, a Convex probe becomes particularly useful.

    A focused transabdominal scan can help an appropriately trained OB/Gynae physician determine fetal presentation, such as:

    Cephalic

    Breech

    or

    Transverse / other lie

    This may be valuable during antenatal visits, late-pregnancy assessment or labour-related evaluation.

    For many clinical questions, having ultrasound immediately available can make it easier to combine physical examination findings with real-time imaging.


    8. Placental Location

    Placental location is an important part of obstetric ultrasound assessment.

    A Convex probe can provide a broad transabdominal view of the uterus and placenta.

    In certain situations, additional transvaginal assessment may be necessary to evaluate the relationship between the placenta and cervix more accurately.

    This again illustrates why TVS and Convex should not always be considered competing probes.

    They complement one another.

    The appropriate approach depends on gestational age, anatomy, clinical question and operator expertise.


    9. Amniotic Fluid Assessment

    Transabdominal ultrasound may also assist trained clinicians in focused evaluation of amniotic fluid.

    When clinically indicated, ultrasound findings can contribute to the assessment of whether fluid volume appears appropriate or whether a formal obstetric ultrasound evaluation is required.

    Current ISUOG guidance for later-pregnancy ultrasound includes evaluation of fetal presentation, placental location, fetal biometry and amniotic fluid as components of obstetric sonographic assessment.


    10. A Powerful Tool for Emergency OB/Gynae Assessment

    Consider an emergency scenario:

    A pregnant woman arrives with abdominal pain and vaginal bleeding.

    Traditionally, the physician might perform the examination and then wait for access to an ultrasound department.

    With a handheld POCUS device available at the bedside, a trained clinician may be able to obtain focused sonographic information immediately and combine it with vital signs, history and examination.

    This does not mean that every handheld ultrasound examination provides a final diagnosis.

    But it can help answer an important question:

    “What do I need to know right now to decide the next clinical step?”

    This question-oriented nature is one of the central strengths of Point-of-Care Ultrasound.


    TVS + Convex: Two Perspectives, One Clinical Workflow

    Think of the two probes as providing complementary perspectives.

    TVS

    Closer. Higher-resolution pelvic assessment.

    Particularly useful for:

    • Early pregnancy
    • Uterus
    • Endometrium
    • Cervix
    • Ovaries
    • Adnexa
    • Pelvic pathology

    Convex

    Wider. Deeper transabdominal assessment.

    Particularly useful for:

    • Obstetric overview
    • Later pregnancy
    • Fetal position
    • Placental assessment
    • Amniotic fluid
    • Broader uterine and pelvic evaluation

    TVS + Convex = A More Complete Point-of-Care Solution for OB/Gynae

    Rather than carrying separate ultrasound systems, a dual-probe handheld solution can allow clinicians to choose the appropriate scanning approach based on the patient in front of them.


    Why Handheld Wireless Ultrasound?

    The transformation is not simply about making an ultrasound machine smaller.

    It is about changing access to imaging.

    A handheld wireless ultrasound can potentially fit into the everyday clinical workflow:

    Patient arrives → Clinical history → Physical examination → Focused POCUS → Clinical decision

    Instead of:

    Patient arrives → Examination → Imaging request → Ultrasound department → Waiting → Report → Return to physician

    Not every patient or clinical question can follow the first pathway, and comprehensive diagnostic examinations remain essential when indicated.

    But for appropriately selected focused examinations, portability can make ultrasound much more accessible at the point of care.


    SonoHealth Handheld Wireless Ultrasound — TVS + Convex

    For OB/Gynae specialists looking to integrate point-of-care ultrasound into everyday clinical practice, SonoHealth Handheld Wireless Ultrasound with TVS + Convex configuration provides two important ultrasound approaches within a highly portable platform.

    TVS Probe

    Designed for close-range transvaginal imaging for applications such as early pregnancy and pelvic assessment.

    Convex Probe

    Designed for transabdominal imaging, providing greater depth and a broader field of view for obstetric and pelvic applications.

    The handheld format allows the ultrasound system to work with compatible smart devices, making imaging more accessible in environments such as:

    • Private consultation chambers
    • OB/Gynae clinics
    • Hospitals
    • Labour wards
    • Emergency departments
    • Bedside examinations
    • Rural and peripheral healthcare settings
    • Mobile clinical services

    The objective is simple:

    Bring ultrasound to the physician instead of always bringing the patient to the ultrasound machine.


    From “I Think” to “I Can See”

    Clinical medicine will always depend on history, examination, experience and professional judgment.

    POCUS adds something powerful to that process:

    Real-time visualization.

    When appropriately trained physicians can see relevant anatomy at the point of care, they may be able to integrate that information immediately with the clinical picture.

    That is why handheld ultrasound should not simply be viewed as a smaller ultrasound machine.

    For many physicians, it can become an extension of the clinical examination.


    POCUS Does Not Replace Comprehensive Diagnostic Ultrasound

    This distinction is important.

    Point-of-Care Ultrasound and comprehensive diagnostic ultrasound are not necessarily the same examination.

    POCUS is generally performed to answer a focused clinical question relevant to immediate patient management.

    A comprehensive diagnostic ultrasound may require:

    • Detailed standardized imaging protocols
    • Multiple measurements
    • Advanced Doppler assessment
    • Detailed fetal anatomical evaluation
    • Specialist interpretation
    • Structured documentation
    • Follow-up examination

    AIUM practice parameters emphasize defined minimum criteria, appropriate examination techniques and documentation for high-quality diagnostic ultrasound.

    Therefore, suspicious, complex or inconclusive findings identified during POCUS should be referred for appropriate comprehensive assessment.

    The goal of POCUS is not to replace specialists. It is to give appropriately trained clinicians another tool for timely clinical decision-making.


    Training Matters

    Buying an ultrasound device does not automatically create a POCUS program.

    Clinical value comes from the combination of:

    Technology + Physician Training + Scanning Technique + Clinical Knowledge + Appropriate Patient Selection

    OB/Gynae physicians using handheld ultrasound should receive appropriate training in image acquisition, anatomy, interpretation, documentation, infection prevention and the limitations of focused ultrasound.

    ISUOG’s dedicated Ob/Gyn POCUS guideline reflects the increasing importance of establishing appropriate standards as point-of-care ultrasound becomes more widely adopted.


    The Future of OB/Gynae Ultrasound Is Becoming More Accessible

    Ultrasound technology has evolved from large machines confined to dedicated rooms to compact systems that can be carried to the bedside.

    For Obstetricians and Gynaecologists, this evolution has special significance because ultrasound is already deeply integrated into the specialty.

    A TVS + Convex handheld wireless ultrasound gives the clinician two complementary imaging approaches:

    TVS for closer pelvic visualization.

    Convex for broader transabdominal and obstetric visualization.

    Together, they can create a practical point-of-care imaging solution for modern OB/Gynae practice.


    See the Patient. Scan at the Point of Care. Decide with More Information.

    The future of women’s healthcare is not simply about more technology.

    It is about putting the right technology in the right hands at the right moment.

    Point-of-Care Ultrasound can help bring real-time imaging closer to the patient—and closer to the physician making the clinical decision.

    SonoHealth Handheld Wireless Ultrasound

    TVS + Convex

    Portable Imaging for Modern OB/Gynae Practice

    See More. Diagnose Faster. Treat Better.

    For product information, physician demonstration, clinical discussion or quotation:

    Unique Medi Trade
    Handheld Wireless Ultrasound Solutions in Bangladesh

    Contact: +880 1717-811312


    Medical Disclaimer

    This article is intended for professional and educational information only. POCUS should be performed by appropriately trained healthcare professionals and used according to applicable clinical guidelines, institutional protocols and local regulations. A focused POCUS examination should not replace comprehensive diagnostic ultrasound or specialist evaluation when these are clinically indicated.










